L.E.D. Transit Kiosk / Smart City Infrastructure
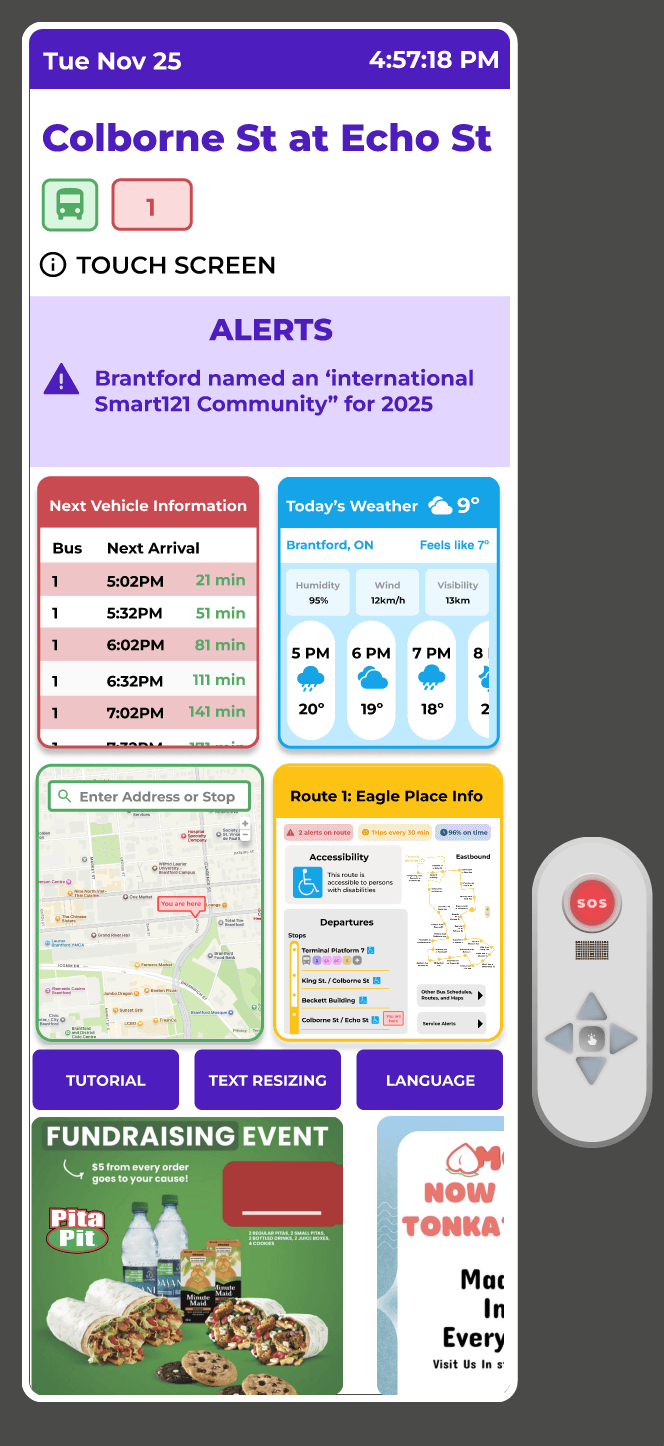
A community smart bus shelter concept with strong public support, until lo-fi testing revealed that its most safety-critical feature, an unlabeled red button, had a 100% initial error rate.
TL;DR
- ①Residents supported the smart-shelter concept (73.1%) but felt unsafe at night (78.3%), safety features had to carry the design.
- ②In lo-fi testing, 100% of participants initially failed the emergency-button task: “Because they don’t say they’re for emergencies.”
- ③Iteration fixed recognition (dual-height physical buttons, labels, silent alarm mode, camera indicator), and a police interview reshaped the feature set.
Context
A bus shelter is safety infrastructure.
The L.E.D. project was a community smart-city brief: a bus shelter with information displays, lighting, and emergency features. A survey of residents surfaced a stark day/night safety split.
The design mandate: the shelter must serve everyone, including children, elderly people, and people in distress, at night, under stress.
66.7%
feel safe at the shelter by day
78.3%
feel unsafe at the shelter at night
the design brief wrote itself
Role
UX research & interaction design, survey, lo-fi testing, iteration, stakeholder research
Type
Course project, MSc UX Design
Duration
One term, iterative cycles
Methods
Community survey, lo-fi usability testing, stakeholder interview (police), ROI modeling
Research questions
Do residents want a smart shelter, and what would make them trust it?
Community survey on needs, safety perception, concept reaction.
Can people actually use the safety features under realistic conditions?
Lo-fi prototype task testing, including the emergency flow.
What do institutional stakeholders require?
Police interview; feasibility + ROI model for the municipality.
Process
Test, fail, fix, repeat.
Survey
Community needs & safety perception
Concept
Smart shelter feature set
Lo-fi test
Task testing, incl. emergency flow
Iteration
Fix what failed
Stakeholder check
Police interview + ROI model
The iteration changelog
1.Dual-height physical buttons
Reachable for children and wheelchair users.
2.Silent alarm mode
For situations where an audible alarm escalates risk.
3.Camera status indicator
Visible recording state for trust and deterrence.
4.Removed medical vending
Cut after the police interview surfaced misuse risk.
The key finding
0%
of participants initially failed to identify the emergency button.
the most critical feature was invisible
“Because they don’t say they’re for emergencies.”
Participant, on why they skipped the button
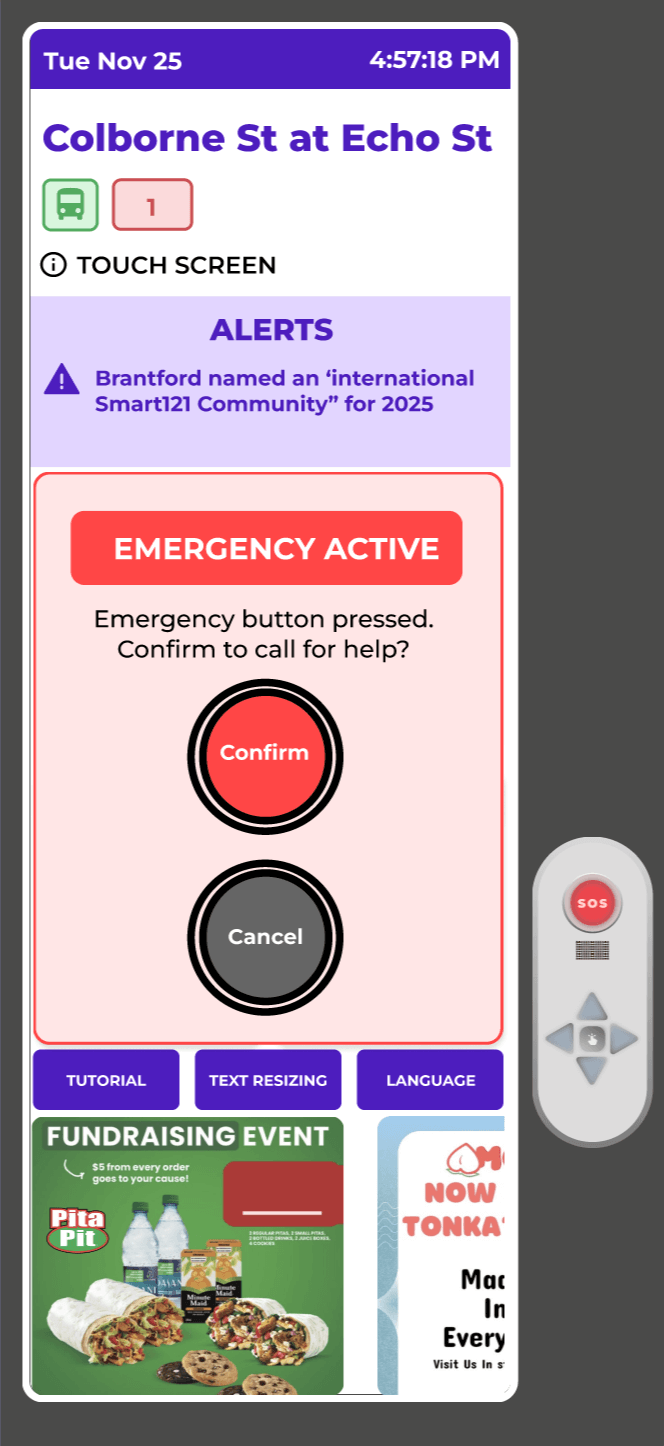
What changed after the 100%.
Before
A button nobody could find
- Plain red button, no label, no affordance
- Didn't notice it at all
- Didn't understand what it was for
- Hesitated to press an unknown control
After
Safety features that announce themselves
- Labeled dual-height physical buttons
- Tactile differentiation for low-vision use
- Silent-alarm option for escalating situations
- Camera status indicator for trust + deterrence
Stakeholders
The police interview that changed the spec.
An interview with the police surfaced misuse and escalation concerns the community survey never could. The medical vending feature was removed outright; silent alarm mode was prioritized for situations where a siren makes things worse; and the camera indicator was reframed as both a deterrence and a trust signal.
I also built an ROI model for municipal decision-makers: cost per shelter against safety and service value, so the research could survive contact with a budget meeting.
“A safety feature that people can’t find is not a safety feature.”
0.0%
concept support
0%
recognition rate in final testing
0
evidence-driven iterations
0
feature cut
Limitations & reflection
What the course scope left out.
This was a course project with a course project’s scope: lo-fi testing only, no hi-fi field deployment; a local and modest survey sample; the police perspective drawn from a single interview; and an ROI model that is indicative, not audited.
The reflection I keep: designing under real-world constraint means the best research finding can be a failure, and the willingness to cut a feature, like medical vending, matters as much as adding any.